Tricuspid regurgitation now has randomised transcatheter evidence behind it, and that has made my heart-team meetings harder, not easier. The question is no longer whether we can shrink the jet; it is whether shrinking it will change the life of the patient in front of us. These six rules are how I decide who benefits, who does not, and when the right answer is no procedure at all.
Rule 1: Grade tricuspid regurgitation beyond “severe”
“Severe” is where modern grading starts, not where it ends. I ask my imaging colleagues to grade the valve as severe, massive or torrential, integrating vena contracta, effective regurgitant orifice area and 3D colour, and to do it when the patient is euvolaemic. A congested patient can look torrential on admission and severe after decongestion.
The grade shapes both device choice and expectations. bRIGHT, a real-world registry of 511 patients from 26 sites, enrolled 88% with massive or torrential tricuspid regurgitation and still reached moderate or less in 81% at one year, with a 19-point KCCQ gain. Leaving mild or moderate residual TR is not failure; leaving torrential TR usually is.
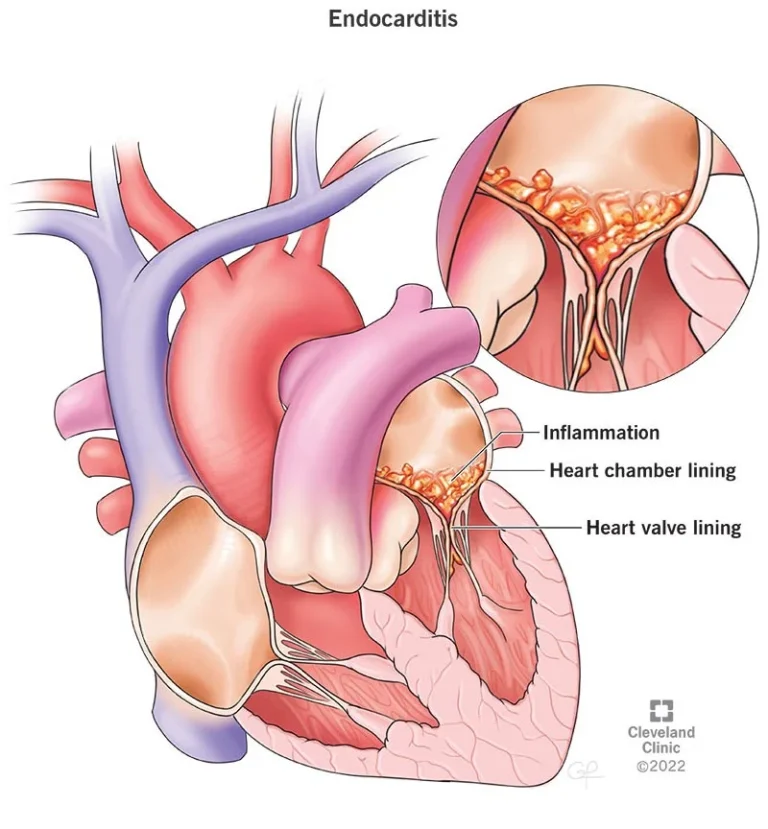
I also name the mechanism of the tricuspid regurgitation: primary leaflet disease, atrial functional (annular dilatation with atrial fibrillation and a relatively preserved RV), ventricular functional (RV remodelling from left heart or pulmonary vascular disease), or lead-related. It predicts prognosis better than jet width.
Rule 2: Stop when the RV or the pulmonary circulation says no
The 2025 ESC/EACTS guideline makes Heart Team evaluation Class I and gives transcatheter tricuspid intervention a Class IIa recommendation for symptomatic high-risk patients on optimal therapy, but only in the absence of severe RV dysfunction and precapillary pulmonary hypertension. I treat both as stop signs, not relative cautions.
Measure pulmonary pressures invasively
In torrential tricuspid regurgitation the Doppler gradient across the valve underestimates pulmonary artery pressure, because flow is laminar and right atrial pressure is high. Every candidate gets a right heart catheterisation on optimised diuretics, and I read pulmonary vascular resistance and the transpulmonary gradient, not the systolic pressure alone.
When the hypertension is precapillary, tricuspid regurgitation is often the pressure-relief valve of a struggling right ventricle. Close it, and the ventricle meets its full afterload overnight.
Read RV function with its loading in mind
TAPSE and fractional area change flatter a ventricle that ejects backwards into a low-impedance atrium. I want RV size, function and coupling to the pulmonary circulation, with CT or CMR when echo windows are poor. A dilated, severely hypokinetic RV with rising bilirubin is no longer a valve problem. It is end-stage right heart failure, and a clip will not rescue it.
Rule 3: Treat lead-related tricuspid regurgitation as a separate disease
A pacemaker or defibrillator lead across the valve demands a different conversation. I first separate lead-induced regurgitation, where the lead impinges on or tethers a leaflet, from lead-associated regurgitation, where the lead is a bystander to atrial or ventricular remodelling. Three-dimensional TOE, and CT when needed, show whether the lead is holding a leaflet open.
If the lead is the culprit, I discuss extraction or repositioning with electrophysiology before anyone plans a clip, and consider leadless or conduction-system alternatives. A commissural lead can defeat T-TEER grasping; a lead behind a replacement valve is jailed permanently, so future ventricular pacing needs another route. Decide this before the procedure.
Rule 4: Use TRI-SCORE to recognise futility in tricuspid regurgitation
TRI-SCORE was derived in 466 patients undergoing isolated tricuspid surgery at 12 French centres. It combines eight bedside variables into a score of up to 12 points: age, NYHA class, right-sided heart failure signs, a high loop-diuretic dose, renal function, bilirubin, LV ejection fraction and RV dysfunction. Its bias-corrected AUROC was 0.753, against 0.629 for EuroSCORE II.
| TRI-SCORE | Observed in-hospital mortality | How I read it |
|---|---|---|
| 0–3 | About 1% | Good candidate; do not delay |
| 4–5 | 14–18% | Proceed only with a clear goal of care |
| 6–7 | 25–32% | Full heart-team debate; benefit uncertain |
| 8 or more | 33–60% | Usually futile; shift towards palliation |
The score came from surgery, not catheter procedures, so I use it as a prognostic anchor rather than a procedural risk calculator. The 2025 ESC/EACTS guideline endorses it for futility assessment. A high score tells me that the kidneys, liver and ventricle are now setting the outlook, and a smaller jet may not move it.
Rule 5: Match the anatomy to T-TEER or transcatheter replacement
When I lean towards T-TEER
- A modest coaptation gap with a central or anteroseptal jet.
- Leaflets long enough to grasp, and a clear TOE view of the valve.
- No lead in the grasping zone.
- A patient in whom avoiding a new pacemaker and extra anticoagulation matters most.
Tri.Fr randomised 300 patients at 24 French and Belgian centres to T-TEER plus optimal medical therapy or medical therapy alone. The Packer composite improved in 74.1% versus 40.6% (p<0.0001), KCCQ reached 69.9 versus 55.4, deployment succeeded in 97.3%, and 30-day major adverse events occurred in 0.7%.
When I lean towards replacement
- Large coaptation gaps, complex or multiple leaflets, or poor grasping windows.
- Massive or torrential tricuspid regurgitation that T-TEER is unlikely to reduce enough.
- CT-confirmed annular and RV dimensions within the device’s range.
- A patient who tolerates anticoagulation and accepts a real chance of pacing.
TRISCEND II randomised 400 patients 2:1 to EVOQUE replacement plus medical therapy or medical therapy alone. The win ratio was 2.02 (95% CI 1.56–2.62), and mild-or-less regurgitation at 30 days was 95.3% versus 2.3%. At two years, presented at ACC.26, control of tricuspid regurgitation stayed near 95% and the symptom benefit held.
The price is real. A new pacemaker or CIED was needed in 24.7%, severe bleeding occurred in 10.4%, and cardiovascular death was 3.1% at 30 days. In a frail patient with fragile conduction or prior bleeding, those figures can outweigh a cleaner echo.
Rule 6: Promise symptom relief from treating tricuspid regurgitation, and refer early
Every randomised trial in tricuspid regurgitation so far has shown benefit in symptoms, quality of life or heart failure hospitalisation. None has shown lower mortality. I say this plainly to patients and families.
What TRILUMINATE Pivotal does and does not show
TRILUMINATE Pivotal randomised 572 patients, mean age 78.1 and 58.9% women, to TriClip T-TEER or medical therapy. The one-year composite win was carried by the KCCQ gain of 12.3 points alone; death, surgery and hospitalisation did not drive it.
At two years, heart failure hospitalisation was 0.19 versus 0.26 events per patient-year (joint frailty HR 0.72, p=0.02). Moderate-or-less regurgitation was 84% after T-TEER versus 21% in controls who stayed on medical therapy. Stroke was 1.9% versus 2.5%, and new pacemakers 5.5%. After year one, 142 of 241 eligible controls crossed over, which blunts any long-term hard-outcome comparison.
TRISCEND II at two years likewise showed no all-cause mortality difference in the primary comparison. The single-arm TRILUMINATE study of 98 patients, not the pivotal RCT, is a sobering companion. At three years 79% had moderate or less regurgitation, NYHA III/IV fell from 76% to 19%, and heart failure hospitalisation fell from 0.56 to 0.14 per patient-year. Yet 27% had died.
Timing: the window closes quietly
The patients who do best are not the ones we send at the end. Once diuretic doses escalate, creatinine and bilirubin climb and the RV fails, TRI-SCORE rises and the benefit shrinks. I want referral when symptoms persist despite reasonable diuretics, not after the third admission with anasarca.
Surgery keeps its place. In the 2020 ACC/AHA guideline, the only Class 1 surgical recommendation for tricuspid regurgitation is tricuspid surgery at the time of left-sided valve surgery when TR is severe, a recommendation written before the randomised transcatheter era. I discuss such cases on my interesting cases page.
For structured learning, the Cardiology Learning Center and the Academy’s cardiology courses go deeper into imaging and selection.
My tricuspid heart-team checklist
- Grade tricuspid regurgitation as severe, massive or torrential once the patient is euvolaemic, and name the mechanism.
- Confirm persistent symptoms on optimised diuretics and full therapy for any left-sided disease.
- Perform right heart catheterisation in every candidate; precapillary pulmonary hypertension means no.
- Assess RV size, function and coupling, with CT or CMR if echo is uncertain; severe dysfunction means no.
- Characterise any lead as induced or associated, decide on extraction, and plan future pacing.
- Calculate TRI-SCORE and document the futility discussion when the score is high.
- Match anatomy: a grasp-friendly valve for T-TEER; large gaps or complex leaflets for CT-sized replacement.
- Weigh pacing and bleeding risk honestly before choosing replacement.
- Set expectations around symptoms, quality of life and fewer admissions, not longer survival.
- Refer before renal and hepatic decline, and revisit the decision if the patient deteriorates while waiting.
References
- Sorajja P, et al. Transcatheter repair for patients with tricuspid regurgitation (TRILUMINATE Pivotal). N Engl J Med. 2023;388(20):1833-1842. DOI
- Kar S, et al. Two-year outcomes of transcatheter edge-to-edge repair for severe tricuspid regurgitation: the TRILUMINATE Pivotal randomized controlled trial. Circulation. 2025;151(23):1630-1638. DOI
- Donal E, et al. Transcatheter edge-to-edge repair for severe isolated tricuspid regurgitation: the Tri.Fr randomized clinical trial. JAMA. 2025;333(2):124-132 (published online 2024). DOI
- Hahn RT, et al. Transcatheter valve replacement in severe tricuspid regurgitation (TRISCEND II). N Engl J Med. 2025;392(2):115-126 (published online 2024). DOI
- TRISCEND II two-year outcomes. Presented at the American College of Cardiology Scientific Session (ACC.26), 2026.
- Lurz P, et al. Real-world 1-year results of tricuspid edge-to-edge repair from the bRIGHT study. J Am Coll Cardiol. 2024;84(7):607-616. DOI
- Nickenig G, et al. Percutaneous edge-to-edge repair for tricuspid regurgitation: 3-year outcomes from the TRILUMINATE study. JACC Cardiovasc Interv. 2024;17(18):2113-2122. DOI
- Dreyfus J, et al. TRI-SCORE: a new risk score for in-hospital mortality prediction after isolated tricuspid valve surgery. Eur Heart J. 2022;43(7):654-662. DOI
- Praz F, et al. 2025 ESC/EACTS Guidelines for the management of valvular heart disease. Eur Heart J. 2025;46(44):4635-4736. DOI
- Otto CM, et al. 2020 ACC/AHA guideline for the management of patients with valvular heart disease. Circulation. 2021;143(5):e72-e227. DOI
Discover more from Dr AM Thirugnanam
Subscribe to get the latest posts sent to your email.